
Small group health insurance refers to health coverage arranged for employers with a limited number of eligible employees and, in many cases, their dependents. Plans designed for small groups typically bundle medical benefits, define cost-sharing between employer and enrollee, and use a single policy or pooled arrangement to spread risk across members. The definition of “small” varies by jurisdiction and insurer; common frameworks categorize groups by employee count for regulatory and pricing purposes. Coverage options available to such groups focus on core medical services, preventive care, and a selection of cost-sharing structures that match employer objectives and workforce needs.
These plans often include distinctions in network design, formulary management, and provider access that influence how members receive care. Employers may contribute a portion of premiums while members pay the remainder through payroll deductions. Administrative features include enrollment periods, eligibility rules, and claims handling. Product variations may include managed care networks, indemnity-style offerings, and arrangements that pair higher deductibles with tax-advantaged accounts. The selection process commonly balances affordability, benefit scope, and the administrative capacity of the employer.

Plan type comparisons often hinge on trade-offs between premium cost, member cost-sharing, and provider access. For example, managed care plans with narrower provider networks may offer lower average premium contributions but require members to use network providers for lower cost-sharing. PPO-style plans may provide greater flexibility to see providers outside a network at higher member expense. HDHPs can reduce employer premium outlays while shifting more near-term claim costs to enrollees, and pairing with an account-based vehicle may support member payment of qualified services. Choice among these options may reflect workforce demographics and employer budget constraints.
Contribution models and cost-sharing design are central considerations for small groups. Employers commonly set a contribution percentage for employee premiums and may choose different contribution levels for dependent coverage. Deductibles, copayments, and coinsurance determine how costs are split when care is received; out-of-pocket maximums cap annual member liability. These elements interact: a lower premium for the group can correspond with higher deductible levels or greater coinsurance, and vice versa. Employers often evaluate how these combinations affect predictability of expenses for both the organization and individual employees.
Eligibility and enrollment mechanics can influence plan suitability for small employers. Common features include employer-defined eligibility criteria (such as minimum hours worked), waiting periods before coverage begins, and defined open enrollment windows. Special enrollment may be available when qualifying events occur, such as changes in household composition. Administrative tasks include verifying eligibility, processing enrollments and terminations, and coordinating premium collection. Plan administrators often consider the trade-offs between more flexible eligibility rules and the administrative burden of frequent changes to membership.
Selection factors for small group plans frequently include network breadth, covered services (such as mental health or specialist care), formulary design for prescription drugs, and ancillary offerings like telehealth. Employers may also assess plan performance data, historical claims patterns if available, and the quality of administrative support provided by carriers or third-party administrators. Non-price factors such as ease of employee communication, clarity of summary plan documents, and the availability of online tools can affect plan acceptance among employees. These considerations may evolve as workforce needs change.
In summary, small group health insurance encompasses a range of plan designs and funding approaches that allocate premiums, deductibles, and provider access between employers and members. Plan selection typically weighs trade-offs among cost predictability, benefit scope, network options, and administrative complexity. Employers and plan administrators often evaluate these elements in the context of workforce characteristics and budget parameters. The next sections examine practical components and considerations in more detail.
Plan types for small groups commonly include managed care models, open-network models, account-compatible plans, and alternative funding arrangements. Managed care models emphasize coordinated care within a defined network, which may reduce routine costs. Open-network models allow broader provider choice but can increase the variability of claims costs. Account-compatible plans pair higher cost-sharing with a dedicated account that members may use for qualified expenses. Level-funded or self-funded arrangements shift certain financial risks to the employer while often including stop-loss features to limit exposure. Each structure organizes coverage around differing balances of network control, member choice, and predictable costs.
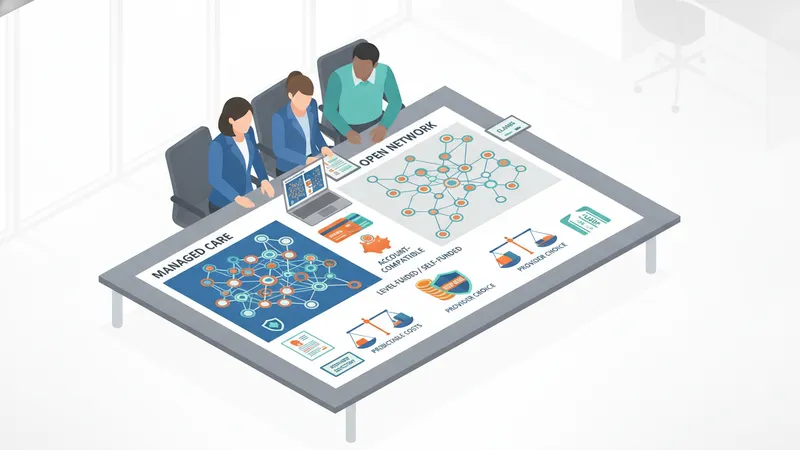
Network design is a core structural feature that may affect utilization and member satisfaction. Narrower networks can deliver lower negotiated rates with participating providers and therefore influence premium levels or employer contribution choices. Broader networks offer more provider options but may include higher negotiated rates and greater administrative complexity in claims adjudication. Network adequacy, referral requirements, and out-of-network benefit rules often determine practical access to care for employees. Employers commonly review provider directories and typical utilization patterns when assessing network suitability for their workforce.
Formulary design and prescription coverage are often integrated into plan structure and can materially affect member cost-sharing. Plans may use tiered formularies that vary cost-sharing for generic, preferred brand, and specialty medications. Prior authorization and step therapy protocols can manage utilization of high-cost treatments, while mail-order options may influence ongoing drug costs. These elements interact with deductible and out-of-pocket policies; for example, some plans apply prescriptions to the medical deductible while others use separate pharmacy cost-sharing. Employers may consider typical prescription profiles in their employee population when evaluating formulary features.
Provider payment mechanisms and administrative arrangements impact plan operation and predictability. Fee-for-service payment with negotiated rates is common, but alternative provider payment models such as bundled payments or value-based contracts may appear in certain markets and networks. Administrative capabilities—claims processing speed, reporting detail, and member support—affect the employer’s operational burden. When evaluating coverage structures, employers may examine historical reporting, projected claims methodologies, and the presence of cost-containment programs such as utilization review or care management as considerations rather than assurances of specific outcomes.

Cost-sharing features define how expenses are split when care is used and include premiums, deductibles, copayments, and coinsurance. Employers typically decide a contribution strategy for premiums that can be a fixed dollar amount or a percentage of the premium; employees cover the remaining premium portion. Deductibles set the threshold before certain benefits are paid by the plan, while copayments and coinsurance determine member costs per service. Out-of-pocket limits cap a member’s total annual liability, providing a form of financial protection. The combination of these features shapes both member financial exposure and the employer’s predictable budget for benefit costs.
Premium trends and predictability are central budgeting concerns for small groups. Premiums may change at renewal based on claims experience, market trends, and plan design changes. Employers exploring alternative funding mechanisms may consider level-funded or partially self-funded approaches that aim to stabilize monthly payments while allowing for potential refunds or higher costs depending on actual claims. Stop-loss insurance is commonly used with self-funding to limit the employer’s exposure to unusually large claims. These funding choices influence cash flow expectations and the allocation of financial risk between employer and plan members.
Design choices can be used to manage both costs and member behavior. Higher deductibles and coinsurance can reduce premium levels but may increase financial barriers to care for some members. Conversely, lower member cost-sharing can encourage earlier use of preventive services and routine care, which may influence longer-term utilization patterns. Benefit design elements such as preventive care coverage without cost-sharing, tiered provider networks, and targeted cost-management programs are tools that can affect how and when care is accessed. Employers often consider the interplay of these levers relative to workforce needs and financial constraints.
Prescription drug cost-management typically supplements medical cost-sharing design and can significantly influence overall plan costs. Strategies include formulary tiering, utilization management protocols, mail-order incentives, and negotiated rebates or discounts within pharmacy benefit management arrangements. Employers reviewing options may consider typical medication use among their enrolled population as part of plan selection. These considerations are pragmatic assessments rather than performance guarantees; actual impact on costs depends on utilization, negotiated terms, and regulatory environments that vary by jurisdiction.

Eligibility criteria define who may enroll under a small group plan and commonly include thresholds such as minimum hours worked or employment status. Employers set these rules within the framework permitted by applicable regulations. Waiting periods may apply, delaying coverage start after employment begins. Open enrollment windows allow employees to join or change elections on an annual basis, while special enrollment events typically permit mid-year changes when qualifying life events occur. Clear documentation of eligibility and enrollment rules reduces administrative friction and helps employees understand when coverage changes can be made.
Administrative processes for small group plans often include data submission to carriers, premium remittance, and reconciliation of payroll deductions. Employers may use in-house payroll and HR systems or external brokers and third-party administrators to manage these tasks. Accurate and timely reporting can affect claims processing, member eligibility, and renewal negotiations. Employers may also encounter requirements for summary plan documents, notifications, and compliance filings depending on jurisdictional rules. These administrative demands influence the choice of carrier or administrator based on capacity to support small-group operational needs.
Communication and employee education are practical considerations during enrollment and plan transitions. Clear summaries of benefits, comparative cost-sharing illustrations, and explanations of network access can help employees make informed selections that align with their needs. Employers may provide enrollment guides, webinars, or decision-support tools to assist employees; the formality and extent of these offerings typically reflect employer resources and the complexity of plan choices. Framing these measures as considerations, not prescriptions, supports realistic planning about administrative investment and expected employee engagement.
Compliance and reporting obligations may vary by jurisdiction and can affect plan operation and employer responsibilities. Required disclosures, privacy rules, and reporting of aggregate plan data are common elements that employers must track. Group size definitions and regulatory thresholds can influence whether an employer must meet specific mandates related to coverage, affordability, or reporting. Employers frequently review applicable regulatory guidance and coordinate with advisors or carriers to ensure administrative practices align with legal requirements and to understand how compliance obligations may affect plan design choices.

Selecting a plan for a small group commonly involves assessing both quantitative and qualitative factors. Quantitative factors include projected premium levels, expected member cost-sharing, and historical or modeled claims patterns where available. Qualitative factors include network composition, administrative responsiveness, clarity of member communications, and ancillary programs such as telehealth or care management. Employers often weigh these elements together, considering the characteristics of their workforce—age distribution, chronic condition prevalence, and typical care utilization—when evaluating alignment between plan features and employee needs.
Renewal and performance review processes are part of ongoing management and typically occur annually. During renewal, employers may evaluate utilization reports, pharmacy trends, and member feedback to determine whether plan adjustments are warranted. Alternative funding considerations, such as moving to a level-funded model, may be revisited in light of historical claims experience. Communication of any changes to employees and updates to administrative processes are practical steps employers consider when managing the ongoing relationship with a carrier or third-party administrator.
Measurement and reporting practices support informed decision-making over time. Employers may track metrics such as enrollment rates, claims per enrollee, and usage of preventive or chronic-care services to identify trends and potential areas for benefit modification. Employee surveys can provide qualitative insight into access and satisfaction. These data serve as considerations to guide plan adjustments and conversations with carriers, rather than guarantees of future outcomes, since results depend on member behavior and external cost drivers.
Ongoing governance and employee engagement strategies can influence plan effectiveness. Employers may institute regular benefit reviews, incorporate employee feedback cycles, and coordinate with advisors to align plan design with organizational goals. Considerations such as phased implementation of benefit changes, targeted education for high-cost conditions, and coordination with wellness or absence-management programs may help manage total cost and employee experience. These practices are pragmatic approaches to plan stewardship and should be tailored to organizational capacity and workforce needs.